The bonus your chart already earned, credited.
GapClose finds and closes HEDIS care gaps and recaptures HCCs for independent primary care — running inside your own environment. Connect by CSV export or a read-only eClinicalWorks link; PHI stays inside your walls unless you open a gate.
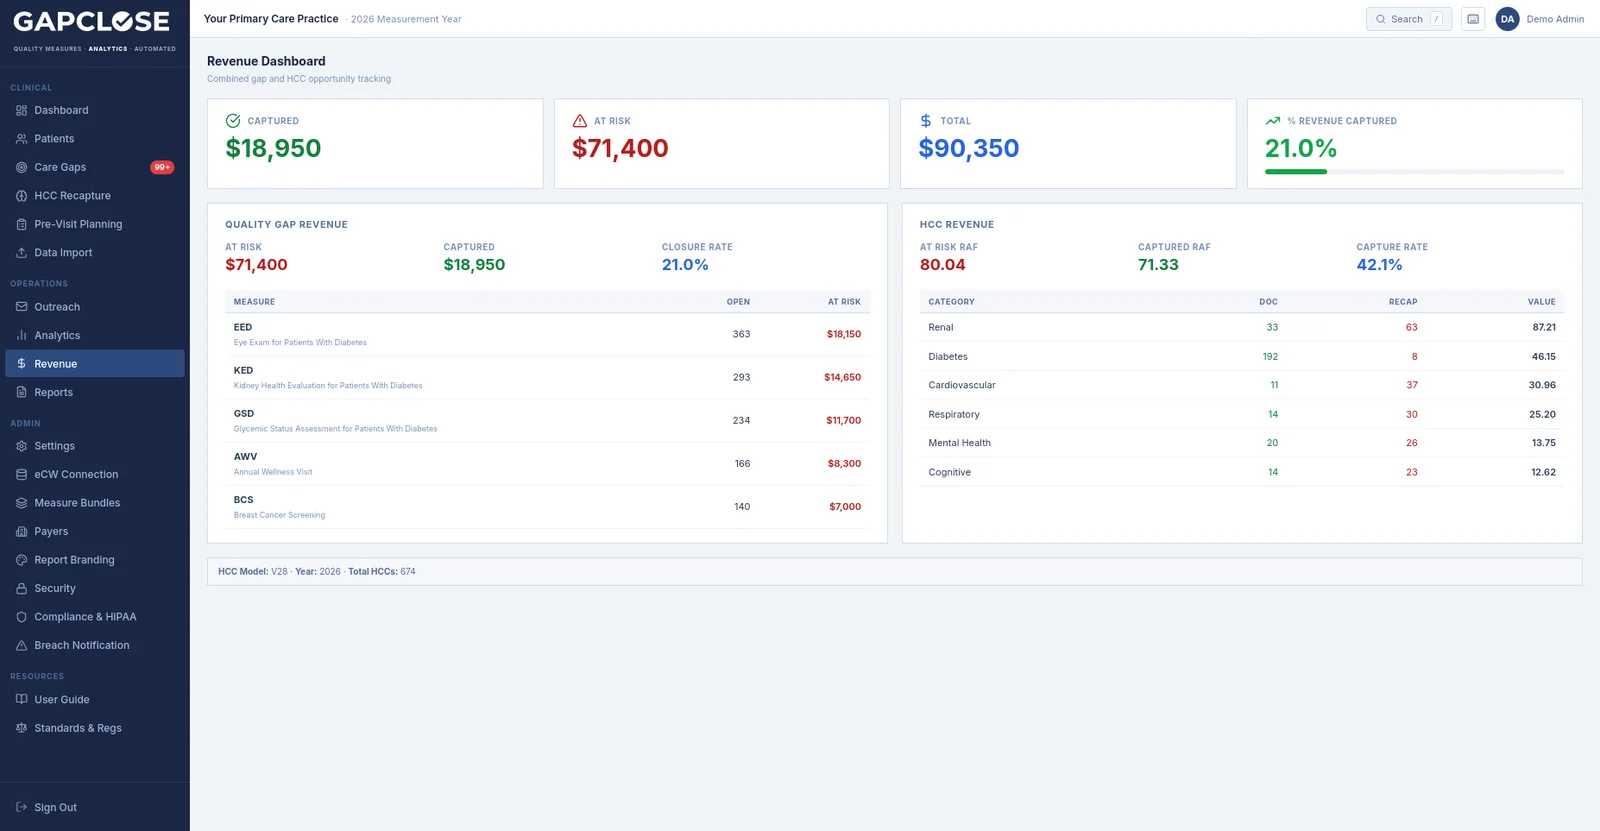
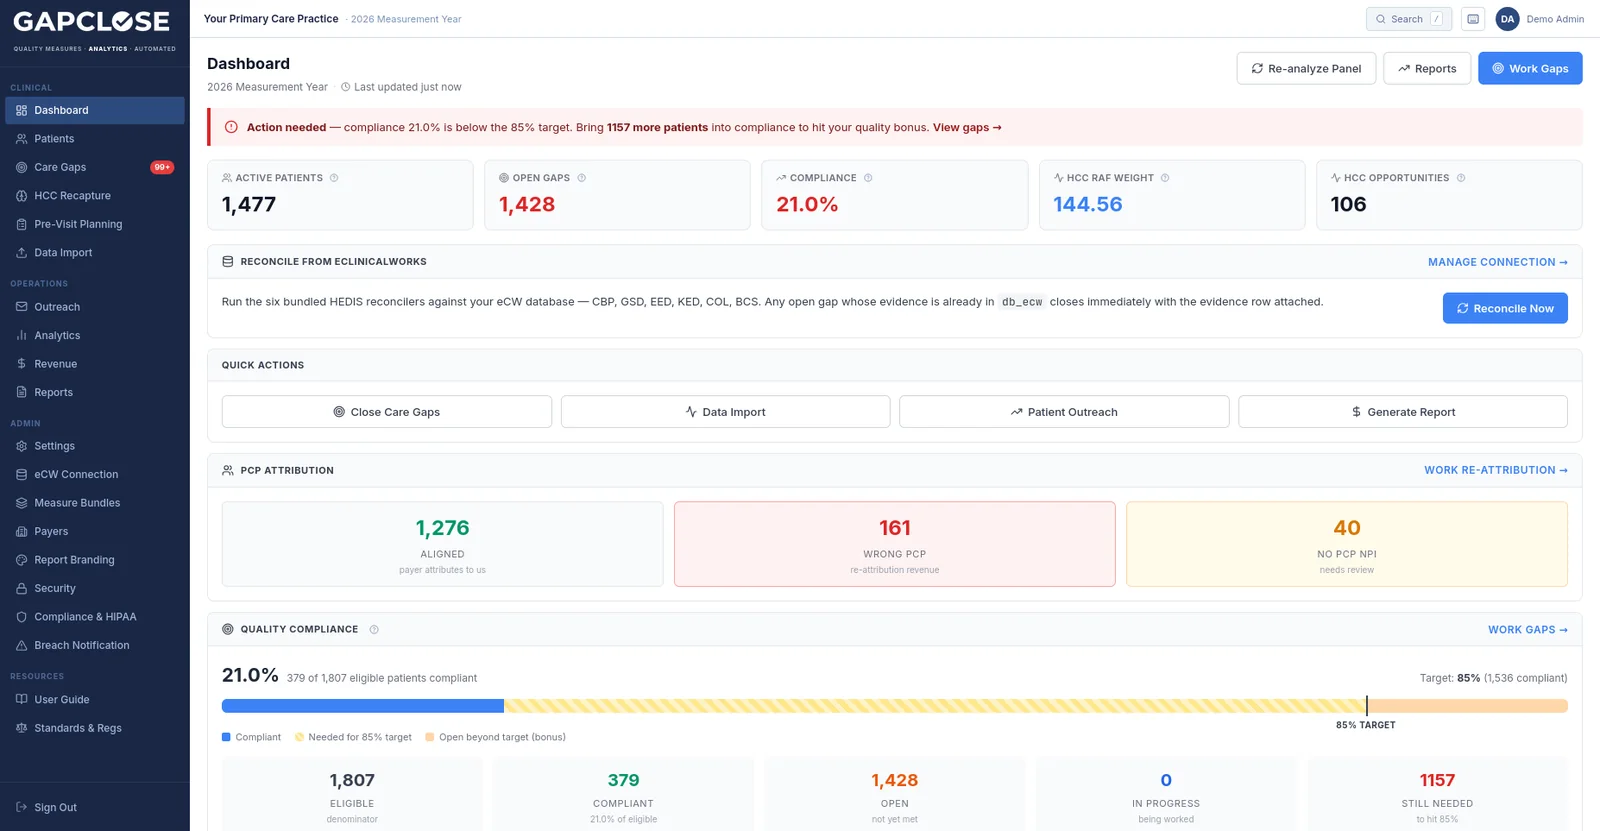
Currently onboarding pilot practices. We confirm BAA coverage before any practice uploads PHI.Explore the live demo
Where the bonus goes missing
Independent primary care practices in Medicare Advantage and value-based contracts can leave thousands of dollars per provider in quality bonus payments on the table each year due to undocumented or overlooked HEDIS gaps.
- Your EHR doesn't track gaps across payers.
- Payer gap files arrive wrong, stale, or blind to evidence that is already in your chart.
- Your staff doesn't have time to manually review 2,000 patients.
Actual dollar impact varies with panel size, payer mix, and existing reporting workflows.
Estimate your range
Set this from your last payer file.
| Annual wellness visit (AWV) | $150–250 |
|---|---|
| Blood pressure (CBP) | $50–150 |
| Diabetes bundle (A1c, eye, kidney)For the three together. | $200–400 |
| Commercial, per gap | $25–150 |
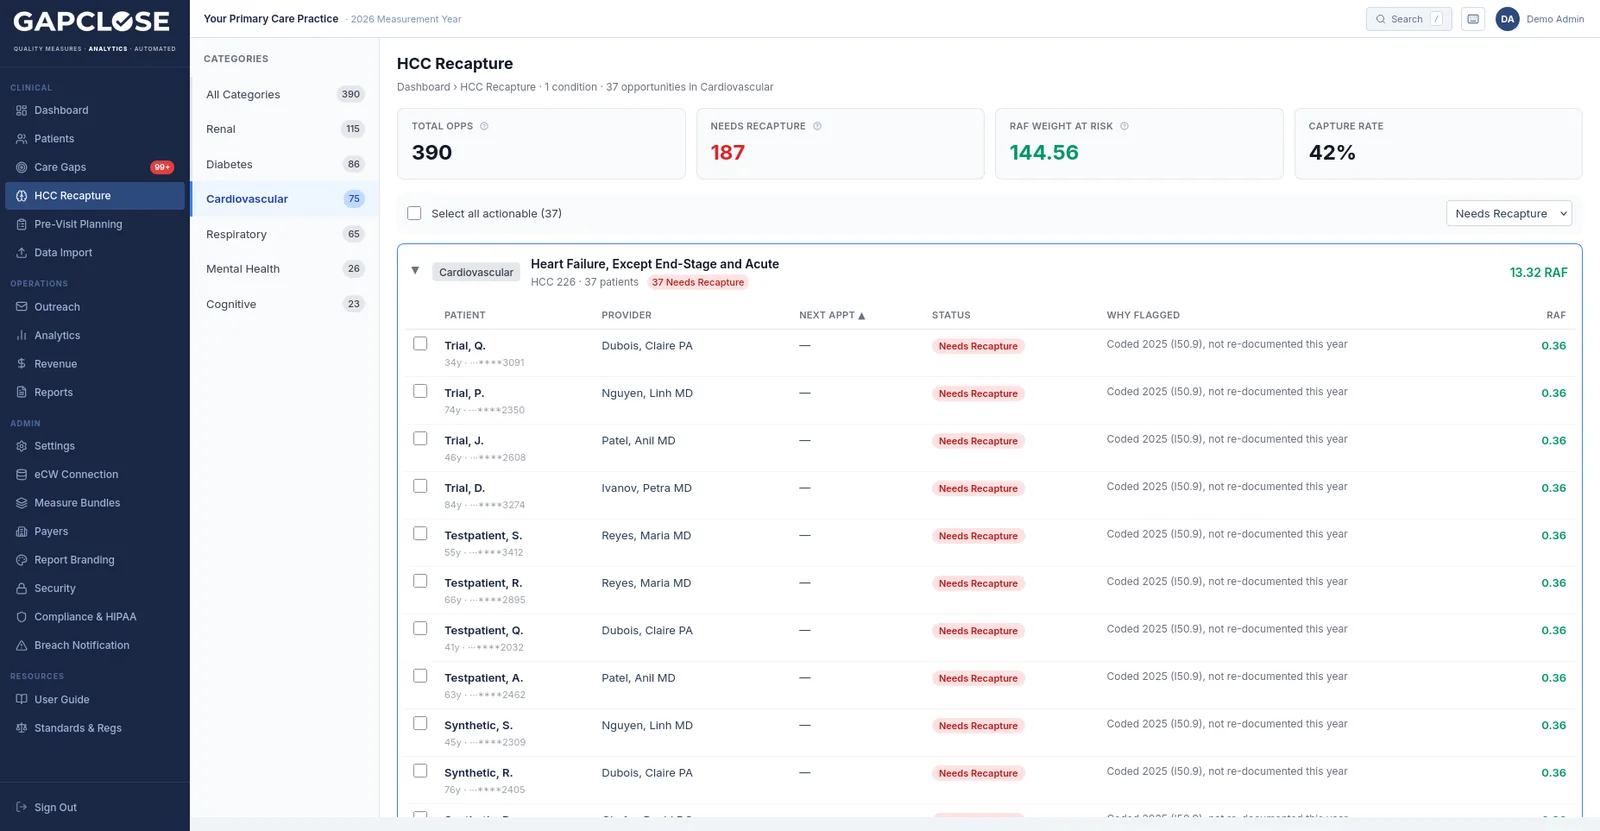
| HCC recaptureNot summed into the range above. | ~$900 per 0.1 RAF |
Industry ranges from public literature, not contract terms; your payer contracts set the actual values.
Inside the walls
Everything that touches PHI runs inside your environment. Only three paths lead out, and each stays shut until you open it.
- PHI held in GapClose's cloud
- none
Runs in your environment
A single-tenant VM in your hypervisor, on-premises or in your own cloud tenant.
AES-256 at rest
Storage-layer encryption on your datastore, attested at install.
Append-only audit log
Patient access and gap changes are recorded and can't be edited.
RBAC + MFA
Five roles, with TOTP required by default for any role with PHI access.
BAA-gated outbound
Each outbound PHI path refuses to send until its flag is set.
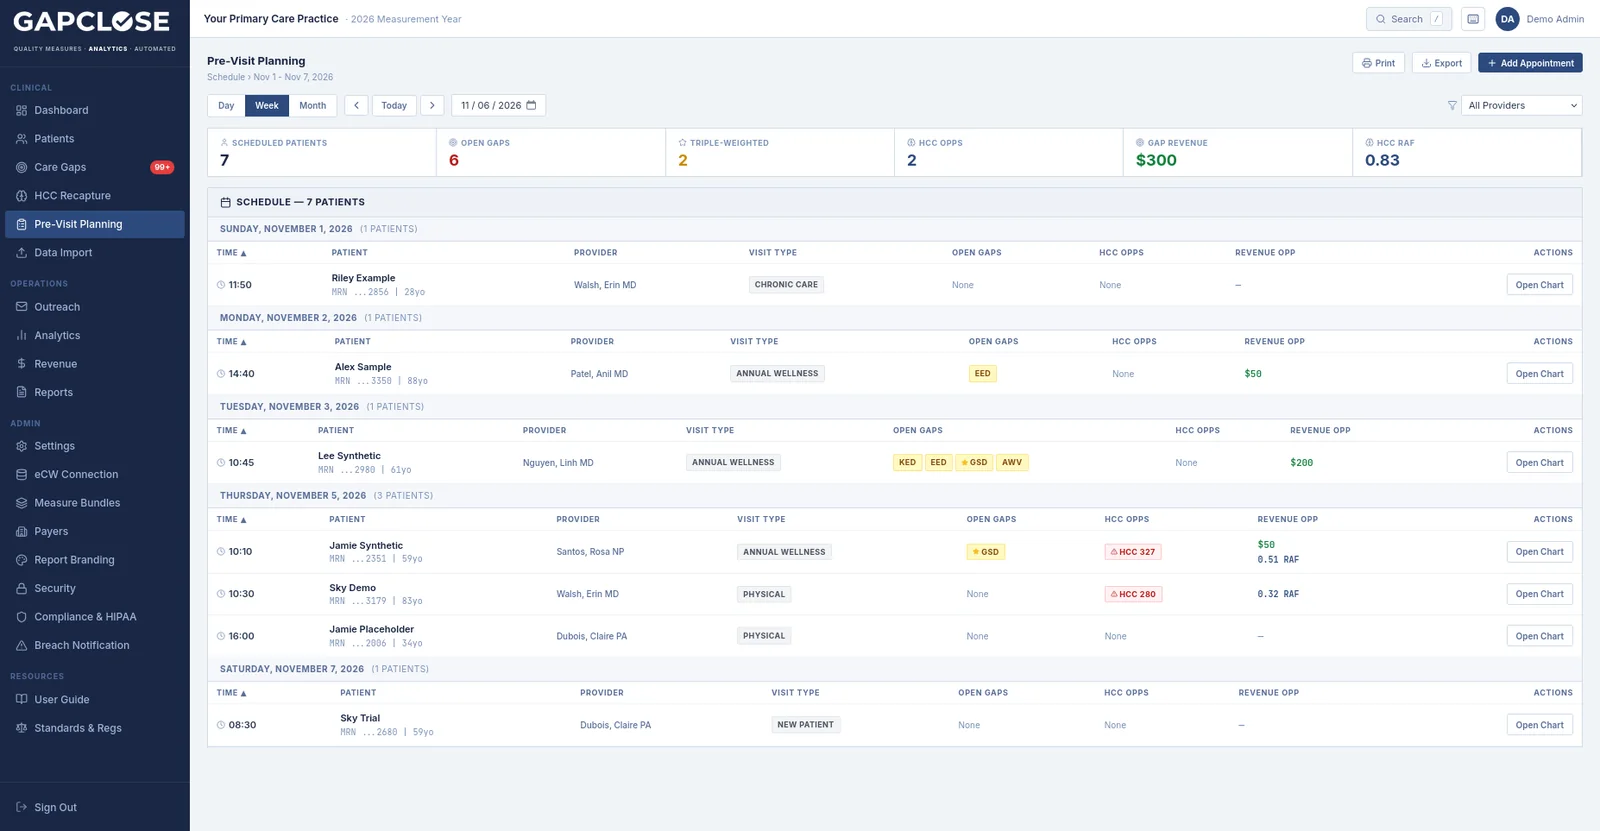
See it running — the live worklist, a read-only smoke test, and a pre-visit huddle
What is running in here
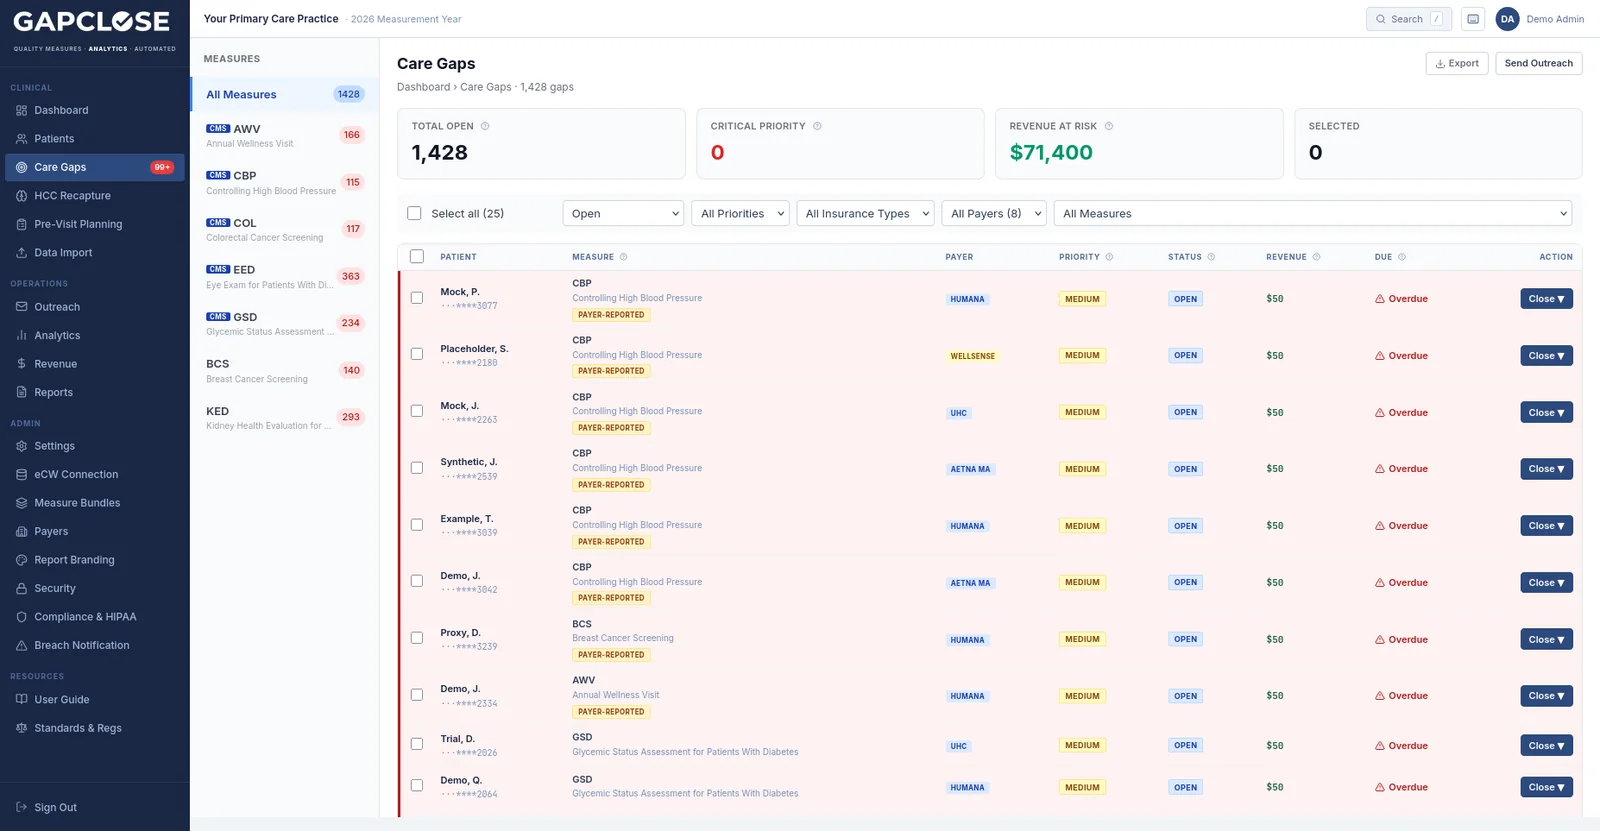
| Patient | Measure | Payer | Priority | Status | Revenue | Action |
|---|---|---|---|---|---|---|
| Mock, P.···3077 | AWV Annual Wellness Visit | Medicare Advantage | High | Needs visit | $250 | |
| Demo, J.···0193 | GSD★ Glycemic Status Assessment | Medicare Advantage | High | Closable | $200 | |
| Synthetic, R.···7306 | COL Colorectal Cancer Screening | Commercial | Medium | Needs visit | $150 | |
| Example, T.···5518 | CBP★ Controlling High Blood Pressure | MassHealth ACO | High | Closable | $120 | |
| Proxy, D.···2640 | EED Eye Exam for Diabetes | MassHealth ACO | Medium | Needs visit | $100 | |
| Trial, D.···9072 | CBP★ Controlling High Blood Pressure | Commercial | Medium | Closable | $75 |
- Reads the
userstablePASS - Reads the
patientstablePASS userstopatientsidentity joinPASSdoctorshas anNPIcolumnPASS- Primary insurance in
insurancedetailPASS - Billing join
enctoedi_invoicetoedi_inv_cptPASS - Blood pressure rows in
vitalsPASS - Lab result path
labdatatolabdatadetailtolabloinccodesPASS diagnosisjoined throughenc.patientIdPASS- Four-source inactive-patient filterPASS
- Epic
- athenahealth
- eClinicalWorksor read-only connector
- Greenway Intergy
- Practice Fusion
- Any CSV export
DOB · date_of_birth · patient_dob → one fieldHeaders differ by EHR. The import wizard maps them once and saves the mapping per source.
| Time | Patient | Open gaps | HCC opps | Revenue |
|---|---|---|---|---|
| 8:00 | MRN ···4821Annual Wellness | CBPGSDEED | HCC 37 | $250 |
| ||||
| 8:20 | MRN ···0193Follow-up | KED | — | $75 |
| 8:40 | MRN ···7306Chronic Care | — | HCC 226 | — |
| 9:00 | MRN ···5520Annual Wellness | COLBCS | — | $200 |
| 9:20 | MRN ···2847Follow-up | CBP | — | $100 |
| 9:40 | MRN ···6615Chronic Care | GSDKED | HCC 38 | $175 |
| 10:00 | MRN ···0978New Patient | — | — | — |
| 10:20 | MRN ···3340Follow-up | EED | — | $75 |
MRN ···48218:00 · Annual Wellness
- Open gaps
- CBPGSDEED
- HCC opps
- HCC 37 · Coded 2025 — recapture
- Last A1c
- 8.4% (03/2026)
- Last BP
- 142/88
- Last colonoscopy
- 2017
- Closable today
- CBPGSD
- Revenue
- $250
Up and running in days
Deployed in your environment. Connect by CSV or a read-only eCW link. Live in days.
- Connect
Connect your data
GapClose runs inside your own environment. Feed it a CSV export from any EHR — Epic, Athena, eCW — or, if you run eClinicalWorks, point it at a read-only database link. PHI stays inside your walls.
- Identify
GapClose identifies the gaps
Every patient scored against the HEDIS engine and the CMS-HCC V28 risk model. Payer-specific criteria applied automatically — on demand or on a nightly run.
- Act
Prioritized worklist + pre-visit huddles
Care coordinators get a revenue-sorted gap and HCC-recapture worklist; providers get a per-appointment huddle sheet. Patient letters in English, Spanish, or Portuguese reach patients through your own SMTP once your team approves them.
- Submit
Close, submit, capture revenue
Document closure, submit supplemental data to each payer over SFTP, and watch revenue impact update as gaps close.
Two kinds of open gap. Two ways to close them.
Many of the gaps a payer file calls open are evidence the payer cannot see. GapClose submits that data and leaves your team only the gaps that need a visit.
Payer gap file, after reconciliation
Track A Chart already has the evidence
- Supplemental fileNCQA-standard CSV
- Payer SFTP gateLeaves your walls here, BAA-gated
- Payer creditNo visit needed
Track B Chart has nothing yet
- Outreach worklistTriple-weighted measures first
- Pre-visit huddle sheetClosable at the visit
Already credited by the payer
- Closed in the payer fileCredited from claims not yet logged
- One-click syncOr investigate the claim
14 HEDIS measures, grouped by how Stars weighs them
Covers the highest-value quality gaps: A1C, blood pressure, cancer screenings, wellness visits, and more. Medicare vs. Commercial thresholds applied automatically.
By CY2026 Part C Star weight
- Weight 3 in CY2026 Part C Stars
- CBP×3
- GSD×3
- Weight 1 in CY2026 Part C Stars
- BCS
- COL
- EED
- KED×3 in 2027
- In payer contracts, not in Part C Stars
- BPD
- CCS
- DSF
- AWVcloses several gaps in one visit
- Also tracked
- LDL
- TCS
- BMI
- FOOT
GapClose vs. enterprise suites
- Where it runs
- GapCloseIn your environment
- Enterprise suitesVendor cloud
- Implementation
- GapCloseDays
- Enterprise suites3–6 months
- EHR integration
- GapCloseCSV or read-only eCW
- Enterprise suitesFull integration project
Pilot pricing — built around your practice
GapClose is onboarding founding pilot practices. Pricing is scoped to your panel size and payer mix under a pilot + annual agreement — no self-serve signup.
- 14 HEDIS measures (expanding) + CMS-HCC V28 recapture
- CSV import or read-only eClinicalWorks direct-DB connector
- Payer file reconciliation + supplemental data submission (SFTP, optional PGP)
- Pre-visit planning huddle sheets
- AI-assisted patient outreach through your own SMTP
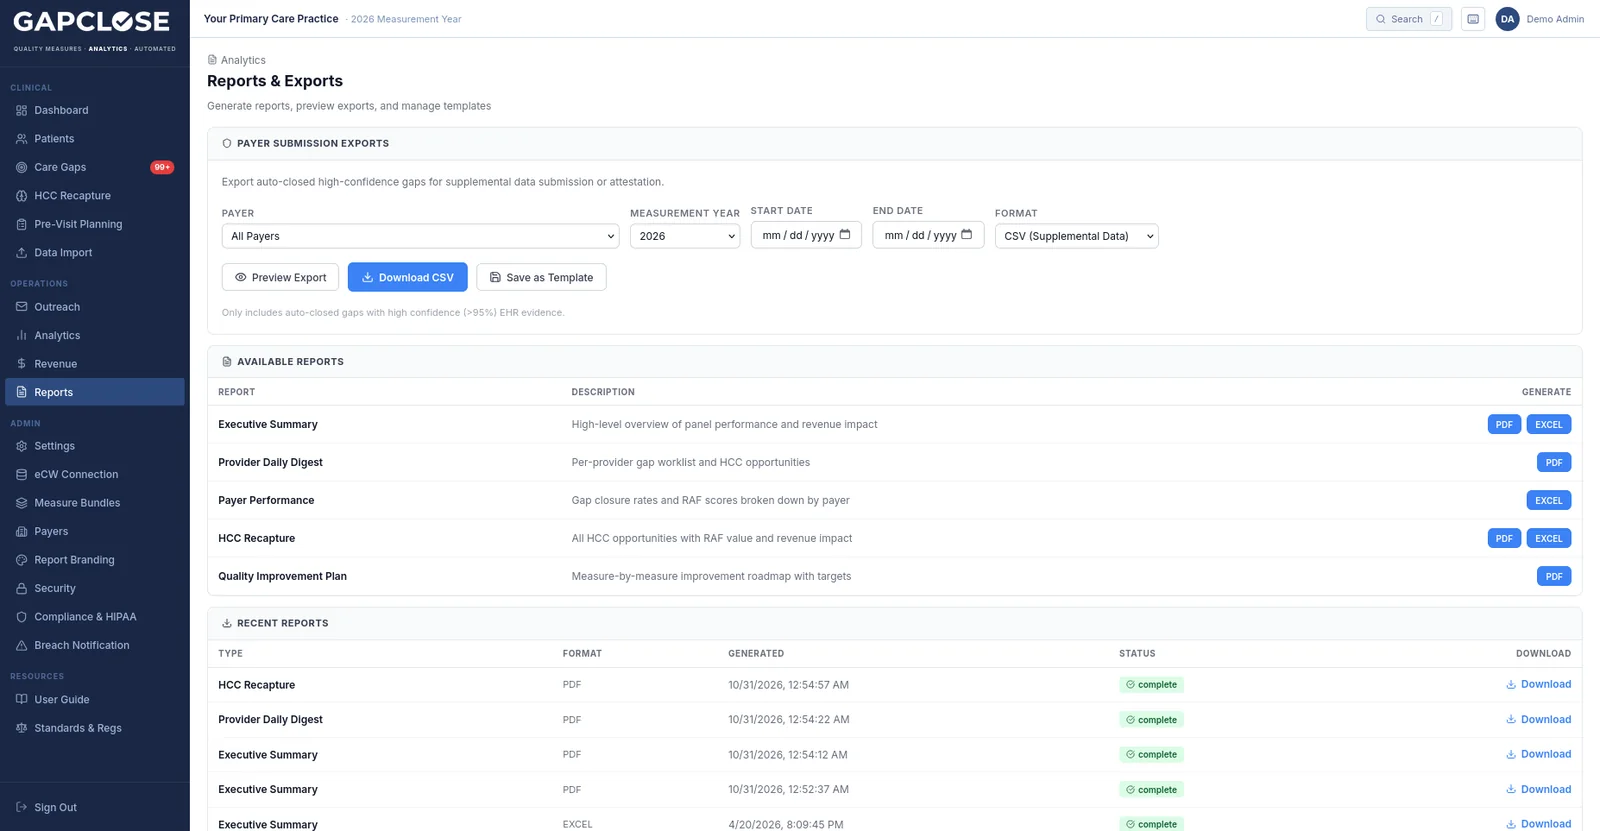
- Analytics, provider scorecards, and report exports
Frequently asked questions
What is HEDIS and why does it matter?
HEDIS (Healthcare Effectiveness Data and Information Set) is the most widely used set of healthcare performance measures in the United States. Payers use HEDIS scores to determine quality bonuses and Star Ratings. Closing HEDIS gaps directly increases reimbursement and improves patient outcomes.
How does GapClose identify care gaps?
GapClose scores your patient panel against 14 HEDIS measures and the CMS-HCC V28 risk model, covering the highest-value quality gaps — A1C control, blood pressure, cancer screenings, kidney and eye exams, wellness visits — plus HCC recapture. It applies payer-specific thresholds, labels each gap by where it came from, and sorts by revenue impact. Analysis runs on demand and on a nightly schedule.
Where does GapClose run, and where does my PHI live?
GapClose deploys as an appliance inside your own environment, so patient data stays on your infrastructure — there is no third-party cloud holding PHI. Outbound paths (AI letters, payer submission, email) are fail-closed until the matching Business Associate Agreement is in place.
Do I need to integrate with my EHR?
No integration project. Start with a simple CSV export from any EHR — Epic, Athena, eClinicalWorks, or anything that exports CSV — and intelligent field mapping handles the column differences. If you run eClinicalWorks on-premises, an optional read-only direct connector reads the database for you and skips the exports entirely.
Do you connect to eClinicalWorks directly?
Yes. Practices on eClinicalWorks can enable a read-only direct-DB connector: GapClose queries the standard db_ecw schema itself — never writing to it — and reconciles gaps and HCCs with no CSV step. Every other EHR works the same way via CSV export.
Is patient data secure? Is GapClose HIPAA-compliant?
GapClose is built HIPAA-conscious and runs in your environment: AES-256 encryption at rest, an append-only audit log, role-based access control, MFA, and PHI kept out of logs and third-party services. HIPAA also requires signed Business Associate Agreements; several sub-processor BAAs are still being executed, so GapClose is currently in pre-pilot status and is not yet accepting production PHI from outside practices. We confirm BAA coverage in writing before any practice uploads real patient data. Contact us to discuss pilot timing.
How long does setup take?
Most practices are live within days. Stand up the appliance, connect your data (a CSV export or the read-only eCW link), and your first gap-and-HCC analysis runs the same day. No EHR integration project, no IT tickets.
What kind of support do you offer?
Pilot practices get direct access to the team. Larger and multi-practice / IPA engagements add dedicated onboarding and a named account contact. Support scope is set in your pilot agreement.
Ready to find out what's sitting in your panel?
Independent practices in Medicare Advantage and value-based contracts leave real money on the table from uncollected HEDIS bonuses each year. GapClose helps you find and close those gaps.